


Anyone who has ever sat in a doctor’s surgery understands a fundamental truth of medicine: you get a diagnosis before you get a treatment plan. The doctor listens, examines, investigates, considers differential diagnoses, weighs evidence, and only then selects from a range of reasonable options. In the past, gender medicine offered watchful waiting, psychological support, or medical intervention. This is not a specific treatment. It is a process. It is the standard medical model that has safeguarded patients for generations.
In gender medicine, this process has been quietly replaced. What is now called the “Gender Affirming Care” (GAC) model is provided in the gender clinics as a competing version of the standard medical process. It structurally privileges a predetermined direction: affirmation leading to social transition, hormones, and surgery, dressed up as a clinical framework. One treatment option replacing others; watchful waiting, exploratory therapy or mental health support for example, has been elevated into the entire process itself. The destination is selected before the journey begins. This is not a minor variation in practice. It is a profound category error, one my organisation, Active Watchful Waiting (AWW), is trying to communicate to AHPRA.
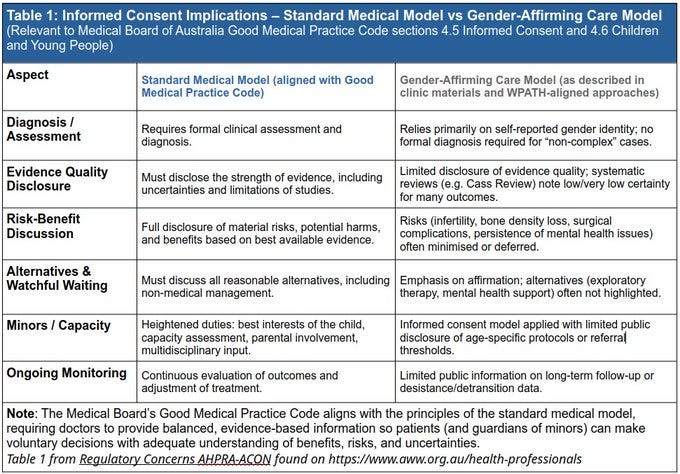
Table 1 from Regulatory Concerns AHPRA-ACON found on
https://www.aww.org.au/health-professionals
I looked at the Medical Board of Australia’s ‘Good Medical Practice: A Code of Conduct for Doctors in Australia’ (October 2020), and found it built around process, not outcomes. It governs how doctors make decisions: how they gather and weigh information, how they obtain informed consent, how they balance benefits and harms, and how they work within the limits of evidence. Section 3.2.7 requires a “reasonable expectation of clinical efficacy and benefit” before recommending treatment. Section 4.5 demands comprehensive informed consent that includes evidence uncertainty, alternatives, and material risks. These are not optional. They are the architecture of safe, ethical medicine, and they’re ignored in the ‘gender affirming care model’.
I submitted a formal compliance assessment and detailed matrix to AHPRA and the Medical Board on 20 May 2026. It shows that gender affirming care, as a model and as currently practiced in Australia, systematically violates at least ten sections of the Code. The matrix compares the two approaches side-by-side. Under the Standard Medical Model, treatment recommendations allow for input from multiple high-quality systematic reviews (Cass Review 2024, University of York reviews, US HHS 2025 review). Interventions are only offered when there is reasonable evidence of benefit. Full disclosure of uncertainty, harms (sterility, sexual dysfunction, bone health impacts, lifelong medical dependency), and alternatives (including psycho-therapeutic approaches) is mandatory. Systematic outcome monitoring is standard.
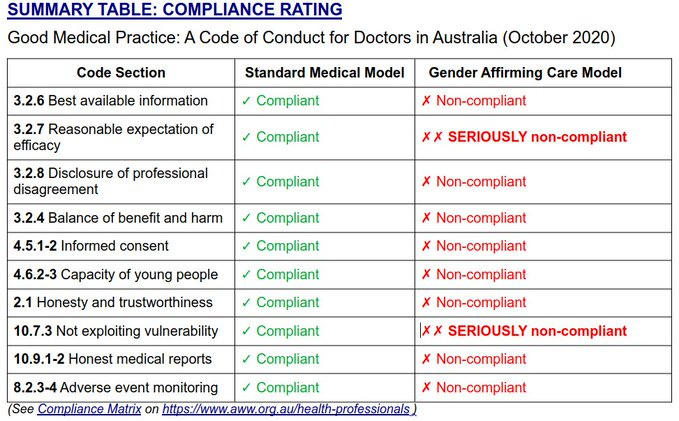
See Compliance Matrix on
https://www.aww.org.au/health-professionals
The GAC model, and the clinics that follow it, fail these tests because of a structural design that mistakes an outcome, gender affirming treatment, for the entire diagnostic process. It dismisses all other treatments as mere options. It privileges affirmation of the patient’s self-identified gender as the starting point and primary goal. This pre-committed pathway leads to reliance on transgender advocacy-aligned guidelines while sidelining contrary systematic evidence of poor-quality data, lack of randomised controlled trials, unknown long-term outcomes, and persistent uncertainty about benefit. Harms are often minimised. Interventions are frequently framed as “life-saving” or “medically necessary” without robust evidence. Informed consent is routinely incomplete. Professional disagreement is not disclosed. These are not isolated failures. They are the predictable consequences of substituting a predetermined protocol for open-ended clinical reasoning.
To understand the inversion, consider an analogy. Imagine oncology adopting a “Chemotherapy Affirming Model.” A patient presents with fatigue, weight loss, and a cough. The clinician affirms the patient’s belief that they have cancer, initiates chemotherapy immediately because “delay causes psychological harm,” and skips biopsy or staging on the grounds that questioning the patient’s self-diagnosis would be invalidating. No responsible oncologist would accept this. The obvious objection, that cancer can be confirmed by biopsy while gender distress cannot. But that only sharpens the point: the less certain the diagnosis, the greater the obligation to investigate before acting irreversibly. It does not merely violate good medical practice in its details; it abolishes the foundational requirement of diagnostic humility*: the ability to approach patient encounters with curiosity rather than conclusive assumptions, before applying irreversible intervention.
The same category error exists in gender medicine. It is important to be precise. “Gender affirming care” as a value is uncontroversial and entirely consistent with good medical practice: treating patients with dignity and respect, and refusing to shame or dismiss their distress. Compassionate, respectful clinical manner is a baseline expectation. The problem lies with the “Gender Affirming Care Model” as a clinical protocol. Conflating compassionate manner with a pre-selected treatment pathway is exactly how the category error became institutionalised. Affirming a patient’s feelings is humane. Pre-selecting irreversible medical interventions as the default response to gender distress, before proper diagnostic assessment, is not.
The compliance matrix submitted to AHPRA sets out the real-world consequences. It demonstrates breaches of core requirements around evidence-based decision-making (3.2.7), informed consent (4.5), balance of benefit and harm (3.2.4), honesty and trustworthiness (2.1), and avoidance of exploitation of vulnerability (10.7.3). These violations flow directly from the model’s structural substitution of outcome for process.
AHPRA regulates process, not specific clinical decisions. Its role is to ensure doctors follow the disciplined framework the Code demands in every other area of medicine. By allowing a model that structurally displaces that framework, the regulator risks undermining the very standards it exists to uphold. The Standard Medical Model does not prohibit transition for carefully selected adults after thorough assessment. It simply insists that any intervention must emerge from proper process, robust evidence, and genuine informed consent, especially when the patients are minors facing permanent changes.
The category error is plain: gender affirming care is not a flawed version of the standard model. It is the abolition of the standard model’s most important feature: diagnostic humility before irreversible action. Restoring the integrity of medical process is not a culture-war issue. It is a patient-safety imperative. Vulnerable young people and their families deserve the same rigorous, evidence-based, ethically sound decision-making process required everywhere else in medicine.
My audits of Australian private gender clinics suggest this is not a theoretical concern. The category error is operational. Across clinic materials, the affirmation model is reflected in service design, public claims, consent omissions, risk minimisation, and the absence of genuinely visible alternative pathways. Clinics present gender-affirming care as safe, evidence-based and clinically standard, while failing to disclose material risks, evidence limitations, long-term uncertainty, fertility consequences, minor-specific safeguards, and non-medical alternatives. That pattern is why my organisation has submitted compliance assessments to regulators under Australian Consumer Law, the Health Practitioner Regulation National Law, the Medical Board’s Code of Conduct, and AusPATH’s own framework.
AHPRA now has the submission and matrix before it. The question is whether it will continue to treat the GAC model as “the standard approach to gender medicine”, or recognise it for what it is: a protocol that replaces open clinical reasoning with a predetermined destination. Professional standards and patient safety require AHPRA to recognise the category error.
Appendix:
See Sky News talking about our complaints “Misleading advertising’: ACON clinic hit with complaints: https://www.skynews.com.au/opinion/misleading-advertising-acon-clinic-hit-with-complaints/video/5c7ad0016a9fa892e8c187ff49fb6e43
Our work also made it to the front page of The Australian 29 May: https://archive.md/jHb0y

Audits, letters etc will be uploaded to https://www.aww.org.au/informed-consent

Endnote: * Diagnostic humility is a clinical approach where a practitioner continuously acknowledges the limits of their knowledge, questions their initial conclusions, and remains open to contradictory information. It serves as a vital safeguard against cognitive bias and premature conclusions.
https://pmc.ncbi.nlm.nih.gov/articles/PMC10838525/
A 2024 study on diagnostic communication with older adults found that when clinicians approached encounters with curiosity rather than conclusion, diagnostic accuracy improved and unnecessary testing decreased (Tran et al., 2024). Clinicians who embrace diagnostic humility demonstrate stronger reasoning, engage more deeply with patient narratives, and are less likely to commit premature closure (Vally et al., 2023).
Please consider donating to support this work. The handful of audits we've completed so far have taken months of full-time, unpaid effort - each complaint letter, matrix and follow-up is painstaking, evidence-by-evidence work. It matters because it documents the unlawful conduct of private gender clinics and holds the regulators to account for failing in their duty to enforce the law and the medical codes of practice. While we've suspended paid work to do it, your help means we can keep going.
Go to https://www.indefenceofchildren.org/ and click on Donation.
Whatever happened to "first, do no harm"? https://lucyleader.substack.com/p/first-do-no-harm
Gender affirming care is all is all lies that cause harm, wrapped up in pink and blue comfort blankie
https://lucyleader.substack.com/p/gender-affirming-care-for-children
I can only imagine what medical historians will be saying about this in another hundred years.